Osborne Head & Neck Institute | Los Angeles
Deep Lobe Parotid Tumors
A Comprehensive Guide to Diagnosis, Anatomy, and Advanced Surgical Treatment
Ryan F. Osborne, MD, FACS | Fellowship-Trained Head & Neck Surgical Oncologist
Medically Reviewed By: OHNI Clinical Staff · Last Updated: November 2, 2026
Overview
What Are Deep Lobe Parotid Tumors?
Deep lobe parotid tumors are rare salivary gland tumors that arise from the portion of the parotid gland located deep to the facial nerve. Unlike more common superficial parotid tumors, which present as visible or palpable masses near the jawline, deep lobe tumors often remain hidden, sometimes growing significantly before detection.
The parotid gland is divided into two main parts: the superficial lobe (located above the facial nerve) and the deep lobe (located beneath the facial nerve and extending toward the throat). Approximately 10% of all parotid tumors originate in the deep lobe, making them uncommon but clinically significant.
Because of their position, deep lobe tumors may extend into the parapharyngeal space, a deep region of the neck adjacent to the airway and vital neurovascular structures. This creates unique challenges in both diagnosis and treatment.
What's a deep lobe parotid tumor?
Unique Challenges
Why Deep Lobe Tumors Are Different

Hidden Location
Deep lobe tumors are often referred to as "hidden tumors" because they do not always present with visible swelling and may grow inward toward the throat.
Patients may first notice:
- A sensation of fullness in the throat
- Difficulty swallowing
- Changes in speech
Complex Anatomy
The deep lobe lies in close proximity to several critical structures, increasing surgical complexity.
Nearby structures include:
- Facial nerve (controls facial movement)
- Carotid artery & internal jugular vein
- Vagus, glossopharyngeal & lingual nerves
Anatomy
The Parapharyngeal Space
The parapharyngeal space (PPS) is a deep neck compartment shaped like an inverted pyramid, extending from the skull base to the hyoid bone. PPS tumors account for less than 1% of all head and neck tumors.
This space is divided into the prestyloid compartment (salivary gland origin) and the poststyloid compartment (neurogenic origin). Deep lobe parotid tumors arise in the prestyloid space and are most commonly salivary in origin.
Classification
Types of Deep Lobe Parotid Tumors
70–80% of parapharyngeal space tumors are benign; 20–30% are malignant.
Benign Tumors
The majority of deep lobe tumors are benign. The most common is pleomorphic adenoma, a slow-growing tumor that may become very large if untreated.
- Most common benign salivary gland tumor
- Slow-growing with well-defined borders
- May extend into parapharyngeal space
Malignant Tumors
A smaller percentage of deep lobe tumors are malignant. Common types include:
- Carcinoma ex pleomorphic adenoma
- Adenoid cystic carcinoma
- Other rare salivary malignancies
Symptoms
Symptoms of Deep Lobe Parotid Tumors
Because of their location, symptoms may differ significantly from superficial parotid tumors.
Common Symptoms
- Sensation of fullness in the throat
- Difficulty swallowing (dysphagia)
- Change in voice or speech
- Visible bulge in the oropharynx
- Ear fullness or pressure
Less Common Symptoms
- Pain (rare in benign tumors)
- Facial nerve weakness
- Weight loss (advanced malignant cases)
Clinical Presentation
- Progressively enlarging oral mass
- Submucosal swelling of the oropharynx
- Extension into the hypopharynx
- Airway function may remain intact
Diagnosis
Diagnosis of Deep Lobe Parotid Tumors
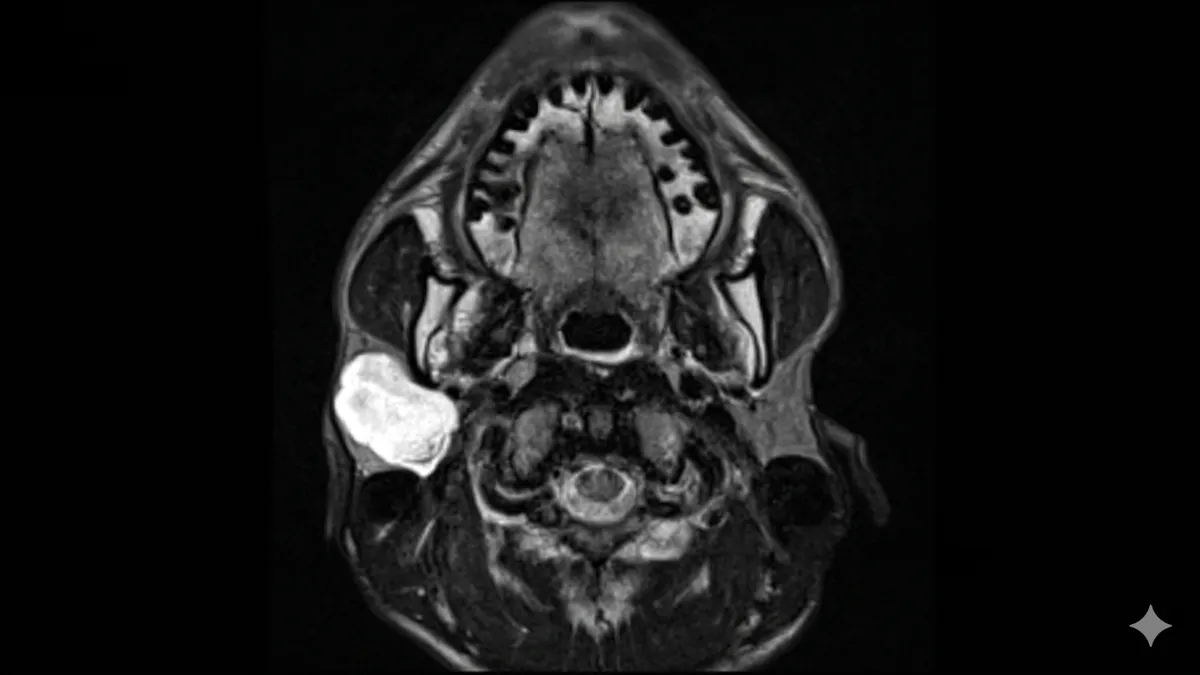
Deep lobe tumors are often difficult to detect because they are not easily visible externally, may not be palpable, and symptoms can be subtle. Imaging plays a central role in diagnosis.

Imaging Is Essential
MRI (Preferred)
Provides excellent soft tissue detail and identifies tumor relationship to the parotid gland.
CT Scan
Useful for evaluating bone involvement and assessing malignant features.
Unlike superficial tumors, biopsy is often avoided initially because the tumor may be highly vascular or close to major blood vessels. Imaging alone is often sufficient to guide surgical planning.
Treatment
Treatment of Deep Lobe Parotid Tumors
Surgical removal is the standard of care. The goals include complete tumor removal, facial nerve preservation, and protection of vital structures.
Transcervical / Transparotid Approach
The most commonly used approach that allows direct access to the tumor, identification and preservation of the facial nerve, and safe removal without unnecessary disruption.
Avoiding Mandibulotomy
Historically, some surgeons performed mandibulotomy (splitting the jaw) to access deep tumors. Modern techniques have made this largely unnecessary, significantly reducing recovery time and morbidity.
Key Surgical Principles
Facial Nerve Preservation
The facial nerve must be carefully identified and protected throughout surgery to prevent facial paralysis.
Complete Tumor Removal
Incomplete removal increases the risk of recurrence and, in some tumors, malignant transformation.
Neurovascular Protection
Surgeons must navigate around the carotid artery, jugular vein, and cranial nerves with precision.
Outcomes
Risks, Recovery & Prognosis
Potential Risks
- Facial nerve weakness (temporary or permanent)
- Bleeding or infection
- Difficulty swallowing (temporary)
- Recurrence if incompletely removed
Recovery Timeline
- Hospital stay: often short
- Return to activity: 1–2 weeks
- Full recovery: several weeks
- Mild swelling and temporary discomfort
Prognosis
- Benign: excellent with complete removal
- Low recurrence when properly treated
- Malignant: depends on type and stage
- Early diagnosis improves outcomes
Real Patients. Real Outcomes.
Patient Reviews for Osborne Head & Neck Institute
Each story reflects what matters most: accurate diagnosis, thoughtful treatment, and outcomes that restore both function and confidence.
Hear From Our Patients
Patient Testimonials
Patients travel from across the United States and around the globe for salivary gland and parotid surgery at the Osborne Head & Neck Institute. Find a story from your state or country and see what the journey looked like for someone in your position.
View Patient TestimonialsExpertise
Why Experience Matters
Deep lobe parotid tumors are among the most technically demanding cases in head and neck surgery. Their hidden location, proximity to critical structures, and need for precise dissection require extensive experience.
Patients Should Seek Surgeons With:
- Extensive experience in salivary gland surgery
- Expertise in parapharyngeal space tumors
- Advanced reconstructive capabilities
PATIENT EDUCATION
Deep Lobe Parotid Tumor FAQs
No. With modern techniques, most deep lobe tumors can be removed without mandibulotomy, reducing recovery time and complications.
Most are benign, but a small percentage are malignant. Imaging and pathology determine the diagnosis.
They are typically identified through imaging (MRI or CT) after symptoms develop, such as a growing mass or parapharyngeal space fullness.
Yes. Surgical removal is the standard treatment for both benign and malignant deep lobe parotid tumors.
The tumor's location beneath the facial nerve and near critical structures like the internal carotid artery requires highly specialized surgical expertise and careful preoperative planning.
Philosophy
Treatment Philosophy
Precision Surgery
Deep lobe tumors require a highly specialized approach that prioritizes complete tumor removal and preservation of function.
Minimally Invasive Mindset
Even in complex cases, the goal is to limit unnecessary disruption, avoid aggressive approaches like jaw splitting, and optimize recovery.
Patient-Centered Care
Each case is unique. Treatment is individually planned based on tumor characteristics and tailored to patient needs.
Further Reading
Related Pages
References
- Thawley SE, Panje WR, Batsakis JG, Lindberg RD. Comprehensive Management of Head and Neck Tumors. 2nd ed. Philadelphia: W.B. Saunders; 1999.
- Cummings CW, Flint PW, Harker LA, et al. Cummings' Otolaryngology – Head and Neck Surgery. 4th ed. Philadelphia: Elsevier Mosby; 2005.

Why Choose OHNI
Not Big Medicine | Personalized, Global Expertise
Many patients assume the best care is found at large, well-known institutions. While these centers offer excellent care, they often operate within standardized systems shaped by regional training models.
At OHNI, Dr. Ryan Osborne offers something fundamentally different: a truly global perspective combined with highly personalized surgical care with experience across five continents, tailoring each procedure to the individual patient, not the system.
Global Perspective
Experience across five continents, applying diverse surgical philosophies and techniques beyond standard U.S. training.
Precision & Preservation
Specialized techniques like Extra-Capsular Dissection designed to minimize invasiveness while protecting the facial nerve.
Patient-First Care
Direct surgeon access, individualized treatment planning, and a focus on both medical outcomes and quality of life.
Proven Outcomes
Patients consistently highlight clear communication, confident surgical decisions, and excellent functional results.
Expert Care for Deep Lobe Parotid Tumors
Deep lobe parotid tumors require specialized evaluation and surgical expertise. Early evaluation allows for accurate diagnosis, safer treatment, and better outcomes.
Become a Patient
Contact the Osborne Head & Neck Institute for expert evaluation and surgical planning.